

Withings, a company that makes connected medical devices, announced on Tuesday that it is developing a miniaturized platform that can analyze urine at home.
The company, which was founded in 2008, is based in France and has offices in the U.S., China and Hong Kong. With its new offering, Withings is seeking to sell a device that taps into the wealth of health information that is present in daily urine.
More than 3,000 metabolic biomarkers can be assessed via urine, which makes it one of the gold standards of health assessment, said Withings CEO Mathieu Leombe. Analyzing these biomarkers can help diagnose and monitor certain diseases like diabetes, chronic kidney disease, kidney stones and urinary tract infection, he pointed out.
Withing’s new device, called U-Scan, sits within a toilet bowl. It consists of a pebble-shaped reader and a changeable analysis cartridge designed to assess specific biomarkers. The device automatically captures small amounts of urine and channels it into the analysis cartridge, which quickly begins chemical analysis. U-Scan automatically transmits readable results via Wi-Fi to Withings’ app.
The device is being developed for the consumer sector as well as the professional medical market. Leombe acknowledged that his company is often compared to other companies like Apple and Fitbit, but these companies have not come out with an at-home urine analysis product yet.
For the consumer market, Withings will sell a U-Scan with an analysis cartridge for women’s monthly cycle tracking and a U-Scan with a cartridge for nutrition and hydration monitoring. These devices will be available for purchase in Europe this year following regulatory clearance, Leombe said.
He also said each U-Scan starter kit will be priced at $499. There is an additional subscription cost of $30 per month, which provides customers with automatic cartridge refills every 3 months.
As for the professional medical market, Withings has some research collaborations underway with Dr. Marie Courbebaisse and Dr. Franck Perez, who are both medical researchers based in Paris. Dr. Courbebaisse is beginning a clinical study to see how the device improves follow-up care for patients with cystine renal lithiasis and uric acid renal lithiasis. Dr. Perez is studying how the device can be used to non-invasively detect bladder and ovarian cancer relapse.
Collaborating with medical professionals to understand the best use cases for U-Scan’s technology will remain a priority for Withings, Leombe declared.
“Presently [U-Scan’s analysis cartridges] can be tailored to analyze a combination of markers such as pH, specific gravity, ketones, vitamin C, albumin and creatinine, but Withings chemistry teams are available to help medical professionals create bespoke cartridges for their use case,” he said.
Photo: Withings

Travelers from China will not be forced to take COVID-19 tests and self-isolate upon arrival in the United Kingdom, according to a report. The Independent said Tuesday that plane passengers arriving in the U.K. from China would have the option to take COVID tests on arrival or not. This is in stark contrast to other countries implementing a different approach amid the recent surge in cases in the Asian giant. Travelers who would test positive for SARS-CoV-2 at Heathrow airport will neither be quarantined nor forced to self-isolate, as well. Meanwhile, in Japan, air passengers who have been in mainland China within the previous seven days will be tested and ordered to quarantine or self-isolate.
As for the United States, the Centers for Disease Control and Prevention (CDC) announced last week that it would require travelers flying from China to present a negative COVID-19 test result within two days before boarding their flights. The new requirement will be implemented starting Jan. 5 in airports based in the People’s Republic of China and the Special Administrative Regions of Hong Kong and Macau with flights bound for the U.S. The U.K. Health Security Agency (UKHSA) explained that it would begin “surveillance” of arriving flights from China on Jan. 8 in response to the recent surge. The operation will involve testing one in five passengers randomly upon arrival at London Heathrow. In Manchester, the only other landing point from mainland China available, COVID tests would not be administered on arrival. “This allows our world-leading scientists at the UK Health Security Agency to gain rapid insight into potential new variants circulating in China. The best defense against the virus, however, remains the vaccine,” health secretary Steve Barclay said.Experts continue to encourage people to get vaccinated amid the ongoing pandemic to lower their chances of being infected with SARS-CoV-2. While the U.K. would not conduct compulsory testing upon arrival, it will not allow passengers who tested positive before boarding in China to travel to the country, Daily Mail reported. Health ministers in the U.K. will be on the lookout for the new variant XBB.1.5, dubbed “The Kraken,” during the random testing of passengers.
A U.K. soldier had to have half of his penis surgically removed after his cancer was misdiagnosed by doctors three times. Gavin Brooks, 45, of Crewe in Cheshire, has opened up about his heartbreaking story amid his final attempt to get therapy abroad for his condition. It all started when Brooks noticed a tight ring of skin around his foreskin. He also developed a lesion on the tip of his penis later on. These forced the army warrant officer to visit military doctors three times in 2021 to have his private part checked, Firstpost reported. He suspected lichen sclerosus, which typically manifests as patchy, discolored, hard skin on the penis. But an army doctor initially told him t was a genital wart.
However, he knew something was wrong when the skin that connected his foreskin to his penis broke and bled, causing him to feel pain whenever he would pee. When he returned for another checkup weeks later, the same doctor insisted it was a wart. But Brooks was not convinced since he has been married for 20 years and only had one sexual partner. He returned to the same medical center for the third time and got examined by a different doctor. But he was told it might be thrush and was given a cream. It was only when he visited a sexual health clinic and was forwarded to a dermatologist who took a biopsy from his penis that he learned he had penile cancer — a rare type of cancer affecting only around 700 men in the U.K. each year. Following his diagnosis, Brooks underwent surgery to have half of his penis removed. He called the remaining half “Frakenweiner” because it does not look like a normal penis. “They lifted my penis up, cut it in half, and took a skin graft from my leg to make a penis head, but it is flat with a hole in it,” he said. Despite the operation, cancer had spread, so he needed another surgery in April to remove lymph nodes in his groin area. He was then subjected to intense chemotherapy in June. Things did not turn out well for Brooks since his cancer spread to other parts of his body. His doctors have since told him that he only has one year left to live, according to Daily Mail. He now wishes to go abroad to receive treatment since chemotherapy on the U.K.’s National Health Service (NHS) did not work for him. He is looking at receiving immunotherapy and proton beam therapy abroad to extend his life and spend more time with his family.
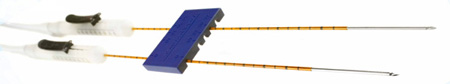
Scientists have discovered that a knife-like surgical device already in use to treat other forms of cancer can also be used in the diagnosis of endometrial cancer in mere seconds.The revolutionary device, called iKnife, “smells tumors” and will help thousands of women get rapid results and eschew weeks of anxiety. The expedited result will also help in the early treatment of cancer patients.The breakthrough came from experts at the Imperial College London and their findings were published in the journal Cancer.“The iKnife reliably diagnosed endometrial cancer in seconds, with a diagnostic accuracy of 89%, minimizing the current delays for women whilst awaiting a histopathological diagnosis,” the team of researchers wrote in the paper. “The findings presented in this study can pave the way for new diagnostic pathways.”
For the study, the researchers collected biopsy tissue samples from 150 women with suspected uterine cancer. Once the tissue sample is collected from the uterus for testing, iKnife uses electrical signals to analyze the smoke that is released when the biopsy tissue is vaporized. Based on its results, the device differentiates between cancerous and healthy tissue.The results from the iKnife were compared with current diagnosis methods.“With its high diagnostic accuracy of 89% and positive predictive value of 94%, one could immediately reassure the person of the very low likelihood of having cancer if the iKnife result is negative and expedite further tests and scans and treatment for people whose biopsies indicate the presence of cancer. This could happen whilst awaiting confirmation from standard pathology, which can take up to two weeks,” Prof Sadaf Ghaem-Maghami, lead researcher at Imperial College London, said, reported The Guardian.Only 10% of women who get their biopsies, suspecting womb cancer, are actually found to have it, as per the outlet. Quick diagnosis with iKnife will provide much-needed relief to the 90% of women, who don’t have the disease.“Waiting for test results is stressful – especially if that test is to find out whether or not you have cancer. When you hear that the ‘c’ word is even a possibility, the days can’t pass quickly enough until a clinician gives you the all clear,” Athena Lamnisos, the chief executive of the Eve Appeal cancer charity, which funded the research, said. “Womb cancer has one ‘red flag’ symptom of postmenopausal bleeding that should always get checked out on a two-week referral from your GP. To wait a further two weeks for the results can be really hard for patients.The research team now plans to undertake a large-scale clinical trial to make diagnosis using iKnife a common practice in the field.“The iKnife has the potential to completely revolutionize the way we manage people seen in the rapid-access clinics with significant abnormal vaginal bleeding who have been referred for potential diagnosis of endometrial cancer,” Ghaem-Maghami said.
A new offshoot strain, XBB.1.5, of the COVID-19 Omicron variant has been found to have “alarming” immunity evasion, which could cause another surge of cases in the United States, according to experts.Dr. David Ho, professor of microbiology and immunology at Columbia University, said the XBB.1 offshoot variant is 63 times less likely to be neutralized by the antibodies in people who have either been infected by COVID-19 or have been vaccinated against the virus when compared to the BA.2 variant. The same is the case with the XBB.1.5 strain.”It is alarming that these newly emerged subvariants could further compromise the efficacy of current COVID-19 vaccines and result in a surge of breakthrough infections as well as re-infections,” Dr. Ho wrote in his findings, which were recently published in the journal Cell.In addition to its high immune evasion, the XBB.1.5. also has a key mutation at site 486, allowing it to bind better to ACE2, which is the door the virus uses to enter human cells. This mutation means the offshoot variant is more infectious.
“The mutation is clearly letting XBB.1.5 spread better,” Jesse Bloom, a computational virologist at the Fred Hutchinson Cancer Center, wrote in an email to CNN.Experts are now warning that the strain’s features could give it the ability to cause another surge of COVID-19 cases in the U.S.As of Friday last week, the U.S. Disease Control and Prevention (CDC) estimated that the XBB.1.5 variant accounted for 41% of new COVID-19 infections throughout December.In northeastern states, the CDC said the offshoot variant is causing about 75.3% of all new cases. Those states include Connecticut, Maine, Massachusetts, New Hampshire, Rhode Island and Vermont.In New York and New Jersey, the XBB.1.5 strain caused 72.2% of cases during the last week of December.As of Tuesday, the U.S. reported a total of 100,845,043 COVID-19 cases since the pandemic began in 2020. Among those, 1,093,971 have died of the virus, according to data from Johns Hopkins University.

Mental health apps skyrocketed in popularity in recent years, offering consumers support in a way that’s convenient and affordable. But there are between 10,000 and 20,000 mental health and wellness apps available for consumers, and not all of them are backed by evidence. So how can people sift through the numerous options to find the right ones for their mental health?
For Dr. Shiri Sadeh-Sharvit, chief clinical officer of Eleos Health and a practicing mental health clinician, there are several things she checks off from her list when considering which solutions to recommend to patients. The first is the startup’s mission.
“Is this company trying to solve a real problem and improve the lives of people in need or the professionals supporting them?” she said. “Or is this a solution searching for a problem? I prefer companies that support the mission of affordable, accessible, evidence-based care that could be scalable.”
Sadeh-Sharvit prefers companies that have teams of experienced professionals with clinical backgrounds. To her, that signals the solutions are likely more ethical and relevant to the field. Next, she checks to see if services offered through the startup are backed by evidence, like cognitive-behavioral therapy. For that, she looks for peer-reviewed papers to ensure the solutions do indeed work and are validated. In this regard, she’d like to see a randomized controlled trial in real-world settings that compare the company’s products to an active control group.
Privacy and security are also a a top priority given the sensitive nature of mental health care. Equally important is user experience because a positive experience can affect how well a treatment works.
Last, but not least, on her checklist is a sustainable business model.
“In order to keep offering services to clients, I want to make sure that they will be able to maintain their financial viability,” she said.
One of the companies Sadeh-Sharvit feels is more grounded in research and follows ethical rules is Woebot, an AI-powered chatbot. A 2017 randomized controlled trial of young adults using Woebot found that the chatbot significantly reduced symptoms of depression compared to the control group. Sadeh-Sharvit said she has colleagues and friends working at Woebot and briefly served as an unpaid consultant for the company in 2017. She also listed SilverCloud and the Veterans Affairs’ self help apps as good examples of mental health solutions.
Sadeh-Sharvit’s comments were echoed by Dr. Don Mordecai, national leader for mental health and wellness at Kaiser Permanente. The integrated health system wants to ensure the members have access to an app that offers mindfulness, as well as real-person support. That’s why the organization works with mental wellness app Calm and mental coaching company Ginger.
When evaluating companies to contract with, Kaiser Permanente prefers they have a certain level of maturity and knowledge of HIPAA and privacy regulations, Mordecai said.
“We’re not super interested in the brand new, coolest-sounding-idea app,” he stated.
Like Sadeh-Sharvit, Mordecai also prizes a sizable volume of data available on the solution’s effectiveness. In other words, a digital product that has some clear clinical data behind it.
“There are plenty of companies I get contacted by all the time who have a good idea, they may have a good interface and they’re looking for somebody they can partner with to do these kinds of studies,” Mordecai said. “That’s generally not us. Because we’re really looking to bring these things in at a certain amount of scale, not spend a lot of time proving out the studies for these companies.”
However, with apps like Calm, there’s a lower bar when it comes to data because it’s teaching mindfulness rather than using clinical principles to improve users’ mental health, Mordecai said. That said, Calm has still done studies on its app, including one that tested its effect in the workplace through a randomized controlled trial. The study found that it improved mental health, sleep and productivity.
Ginger — which merged with mindfulness company Headspace in 2021 to create Headspace Health — has also conducted extensive research on its services. A 2021 study determined that 47% of Ginger users saw a decrease in anxiety symptoms. In addition, a 2019 study on Headspace found it reduced anxiety by 19% and depression symptoms by 29%. The conjoined entity recently put out a call to third-party researchers to conduct more studies on how its company affects mental health and wellness outcomes.
When doing this research, it’s important that the treatment group is sizable and diverse, said Katie DiPerna Cook, senior vice president of partnerships at Headspace Health.
“We need to make sure that we’re not just studying those who are more likely to access care, but that we’re really expanding to a broader population,” she said.
She added that companies should be continuously testing their products.
“I think that as a digital mental healthcare provider, we have such a responsibility to be studying outcomes and making sure that we’re getting people better faster … It’s not just one and you’re better,” Cook said. “We need to be studying and following people over time.”
But a lot of companies don’t conduct this kind of rigorous research on their products. Instead, many are turning to “Mickey Mouse trials,” declared Deepak Gopalakrishna, CEO of OxfordVR. The virtual reality company treats severe mental illness and recently merged with BehaVR.
“When you go to most digital technologies’ websites, you see ‘trials’ that are like 15 to 20 patients, certainly not big enough to qualify for anything statistically significant, the appropriate analysis,” he said. “That data has not been done, the population size isn’t big enough, the population isn’t the right population. The endpoints selected don’t actually back up the claims that people are making in the market.”
Other indicators that show a study isn’t robust are those that confuse correlation with causation, as well as those that rely on incentives to get participation, according to Jennifer Gentile, senior vice president of clinical innovation at Ieso. She is also an attending psychologist at Boston Children’s Hospital.
“[A] concerning factor is when study participation and completion is heavily incentivized,” she wrote in an email. “It worries me whether patients will use the tools without incentives.”
Common incentives for research participants include cash payments and gift cards.
Whatever be the process for choosing a behavioral health company, the work doesn’t end with the selection.
“This should be a dynamic, continuous process,” Mordecai said. “Part of that is us saying, ‘This app is really keeping up. They’re refreshing it, it’s super popular. But this other app doesn’t seem to be grabbing people anymore. When we look at the interface and the materials, they don’t seem to be investing in it.’ That’s one criteria where we might say ‘Well, it’s time to move off from that one.’”
Photo credit: Bohdan Skrypnyk, Getty Images

The challenges in treating microbial infections aren’t new. For years, the medical community has grappled with bacteria becoming drug-resistant and viruses evolving faster than we can generate vaccines. But the Covid-19 pandemic presented a new set of challenges, showing us both what’s possible in terms of speed of response and what we need to do better to prepare for the next one. A central lesson might be that we need to move away from the idea of managing a single “bug” with a single tool – it will take a collection of approaches working in concert to fully wrap our arms around a given problem.
To this end, there’s been exciting work around new strategies to supplement standard care, including the antimicrobial effects of nitric oxide (NO), a naturally occurring molecule with documented antiviral, antibiotic, and antifungal properties. While the first therapeutic approval of NO in 1999 leveraged its vasodilatory effects for hospital treatment of blue baby syndrome (persistent pulmonary hypertension of the newborn), another body of research over the years has illustrated its robust antimicrobial effects, including a 2004 study showing its ability to neutralize the coronavirus of the time, SARS-CoV. Delivering the molecule in a safe and convenient enough route (without the need for pressurized gas cylinders) and at the right dose for everyday use had been the larger challenge.
Luckily, a number of research groups have been working on this very issue, developing novel methods to generate NO for new therapeutic applications. Some have developed “tankless” systems, which use electricity to generate inhaled NO for use in hospitals or homes. Others are working on user-friendly methods to deliver NO topically. One of these involves storing and releasing NO from polymers to treat viruses spread by direct contact, including human papillomavirus (HPV) and the common children’s skin infection molluscum contagiosum, as well as fungi and yeasts that infect skin and nails. Another group has evaluated the antibacterial effects of NO released from biopolymers, finding that it kills a variety of bacteria and improves susceptibility in antibiotic-resistant bacteria. One academic research group found that an NO-releasing nanoparticle platform can greatly reduce the incidence of C. albicans infection and accelerate healing in a mouse model of burn wounds.
Importantly, given the current pandemic and the future viral pandemics most experts believe we’ll see in our lifetimes, topical NO delivery also has also been effective against airborne viruses, including SARS-CoV-2. One company is researching a nasal spray that induces nasal cells to produce NO, in the hopes that it may serve as a prophylactic. Our own group has developed a compact delivery system that generates NO right when the user activates it. One of its applications, an NO-releasing nasal spray, has shown promise against SARS-CoV-2 and its variants in both laboratory and clinical studies, including rapid viral load reduction in a Phase 3 study. Various research groups have also demonstrated the effectiveness of NO against a number of other respiratory viruses, including flu, rhinoviruses, and RSV.
Part of what makes NO such a promising antimicrobial is that it works through several mechanisms of action (MOA). Against coronaviruses, these include blockage of entry into nasal passage cells and inactivation of the virus via conformation changes to the spike proteins and proteases, which lead to rapid reduction in viral load. The molecule also has several MOA in single-celled organisms, including DNA damage and inhibition of DNA repair, as well as lipid damage via lipid peroxidation, among others. These mechanisms make NO an effective antimicrobial, able to stand up to evolving variants and unlikely to lead to antimicrobial resistance (AMR). Topical NO also has a demonstrated safety profile – a key benefit of topical use is that it lacks systemic absorption, as measured by changes in methemoglobin or systemic vital signs like blood pressure, so it’s unlikely to be associated with systemic side effects or interactions in the body.
The addition of NO-based strategies to our existing armamentarium has important real-world implications. With most countries transitioning from “pandemic” to “endemic” approaches to Covid-19, adding new therapeutic tools for both prevention and treatment is critical. We’re starting to see some scientific and public interest in strategies beyond systemic vaccines, with the approval of antiviral medications and increased research into nasal vaccines. But these tools have their own drawbacks: oral antivirals can have a “rebound effect,” and while nasal vaccines make sense logically, early attempts haven’t been effective and may have the same vulnerabilities to evolving variants that systemic vaccines do.
Generally, strategies to treat a single “bug” with a single tool have limitations, which is why innovative adjunct methods are so greatly needed. Nitric oxide can be an elegant and effective addition, not to replace conventional methods, but to work alongside them. As we prepare for the next pandemic, we’ll need tools to bridge the gap while vaccines are being generated – while mRNA vaccine production is relatively fast, many people can get sick and die during the waiting period. In addition to viral pandemics, AMR is one of the most urgent global health concerns: Projections suggest that AMR may kill 10 million people annually by the year 2050 and cost $100 trillion globally. At present, we are poorly poised to change that trajectory. Nitric oxide’s antibacterial properties could help reduce the excessive use of antibiotics that has contributed to drug-resistant bacteria.
All in all, NO is a strong candidate to help address many types of infection, as its delivery is adaptable across therapeutic applications with controlled dosing. The global healthcare community generally needs more agents that are effective and safe across populations, including the elderly, children, and immunocompromised individuals, and are easily transported and stored. While more work needs to be done, the current research into new delivery platforms for NO is extremely promising. We hope to see the molecule play an increasingly prominent role in treatment and prevention strategies for common infections – and in so doing help provide greater access to healthcare globally.
Photo: Olemedia, Getty Images
For gene therapy to achieve its potential, biotech companies need to diversify the range of tissues that can be targeted by these treatments. Capsida Biotherapeutics is developing technology that could enable delivery of a gene therapy to cells of the central nervous system. Now Eli Lilly is paying $55 million to kick off a multi-drug R&D alliance, making it the latest pharmaceutical industry partner to sign on with the startup.
The agreement announced Wednesday is with Lilly’s gene therapy subsidiary, Prevail Therapeutics. In addition to the $55 million upfront payment, Prevail agrees to participate in the next financing round of Thousand Oaks, California-based Capsida. Prevail’s payments for research and development as well as milestones could bring the startup up to $685 million more.
Gene therapies are mainly delivered to their cellular destinations carried aboard adeno-associated viruses (AAV). These engineered viruses preferentially target liver cells. Capsida works with capsids, the protein shells that envelop a gene therapy. Engineering capsids in certain ways is intended to optimize their ability to target particular tissues.
Capsida, based on technology from the California Institute of Technology, uses machine learning to screen engineered capsids in order to find the ones that can address desired tissue types, such as those of the central nervous system (CNS). The biotech claims it can engineer capsids that target a single organ or multiple organs simultaneously while also limiting exposure to organs that are not targets of the therapy. That capability could improve the safety of AAV-delivered gene therapies. Delivery to non-target cells can trigger adverse effects.
Specific disease targets covered by the pact were not disclosed. But the deal calls for Prevail to use Capsida’s technology to identify and develop capsids that are paired with genetic cargo from Prevail. That resulting gene therapies will be directed to targets that are known to cause CNS disorders.
The deal gives Capsida the option to participate in the development and commercialization of one of the partnered programs. For all of the programs covered under the alliance, Capsida will take the lead on capsid discovery. Prevail is responsible for preclinical research and studies of the gene therapy candidates with the therapeutic payloads.
“Prevail’s expertise in neuroscience, gene therapy R&D, and access to Lilly’s world-class commercialization capabilities complements Capsida’s fully integrated approach, including our next-generation AAV engineering platform,” Capsida CEO Peter Anastasiou said in a prepared statement. “Prevail and Capsida are committed to developing highly effective and safe gene therapies that have the potential to be transformative for patients living with serious CNS diseases.”
The agreement with Prevail is similar to a deal Capsida has with AbbVie. That alliance unveiled two years ago covers the development of gene therapies for three undisclosed CNS targets. AbbVie paid Capsida $80 million up front and made a $10 million equity investment in the startup. Amyotrophic lateral sclerosis and Friedreich’s ataxia are the disease targets for Capsida’s alliance with CRISPR Therapeutics.
Lilly has become a more active dealmaker in its effort to beef up its gene therapy prospects. Prevail joined Lilly two years ago via an $880 million acquisition. A Parkinson’s disease gene therapy is Prevail’s most advanced program. Late last year, Indianapolis-based Lilly paid $487 million to acquire Akouos, a biotech developing a gene therapy for an inherited form of hearing loss.
Photo: Jolygon, Getty Images

It’s critical for medical science liaisons (MSLs) and medical affairs teams to build lasting relationships with key opinion leaders (KOLs). And in our increasingly digital-focused world of healthcare, regional and local influencers matter just as much as traditional KOLs. These relationships have a direct impact on the success of clinical trials, bringing treatments to market, and reaching broader and more diverse patient populations.
Yet, recent industry data shows that MSLs struggle with identifying and accessing KOLs. Compounding this struggle? MSLs rarely get access to fresh KOL lists — these are usually handed down over time throughout the organization, or only include KOLs at big academic medical centers.
But, as the saying goes, you don’t know who you don’t know … right? In this case, wrong.
Whenever we raise the topic of the importance of “new” KOLs, we are often asked the same questions: Who are they? Why are they important? How and where do I find them? And, how can I forge meaningful relationships with them?
Let’s answer some of these frequently asked questions that MSLs have when it comes to identifying and engaging with undiscovered KOLs.
FAQ: What’s the difference between a treatment leader, KOL and DOL?
Answer: Let’s break down all the different types of KOLs. Traditional KOLs are established physicians or PhDs well-known in their fields. They regularly publish papers, attend and speak at conferences, and sit on multiple advisory boards. They are very public and often cited.
Digital opinion leaders (DOLs) can be anyone from healthcare professionals to patient advocates or researchers who have an influential digital voice in the community. DOLs want to educate, engage, and challenge their followers in the name of science – while also positioning themselves as experts. They are skilled at communicating digitally and are building expertise and credibility to back up their statements. Research shows that discovering digital opinion leaders (DOLs) is even harder than finding traditional KOLs, with 66% of MSLs sharing this frustration.
The challenges often lie with finding new and different KOLs, who, on the other hand, are thought leaders (digital or otherwise) but who are up and coming or simply not as well known as the more veteran KOLs – they are clearly talented, but haven’t yet had the chance to prove themselves. They may be publishing, but they haven’t developed a body of work over decades that distinguishes them as a KOL or DOL, like their more well-known counterparts. Or, perhaps they are early in their careers or are the “shy type” who aren’t vocal and have flown under the radar.
All of these opinion leaders are like pieces to a puzzle – together they bring more value and a fresh perspective than when they stand alone.
FAQ: Why is it important to update stale KOL lists?
Answer: Medical affairs teams typically target the traditional KOLs that are already well-known in their fields. But, these experts don’t always reflect the demographics of real patients or physicians. This lack of representation can carry through to everything from clinical trials to treatment distribution, contributing to the ongoing inequity in healthcare.
The biggest value in uncovering these thought leaders of tomorrow is in their diversity of thought. They have the potential to be the next big influencers, bolster awareness of clinical trials, and truly impact the future healthcare for the better.
FAQ: Is one type of KOL more valuable than another?
Answer: There are a few types of KOLs that MSLs may want to focus on. The first is what we call “rising stars.” These opinion leaders are the next heads of departments and presidents of medical societies. By building relationships with these so-called junior KOLs early, you’ll have that connection established by the time they become more well-known, and they’ll be more responsive to your requests. The funny truth is that most “rising stars” are not as young as you might think. With med school, residency, fellowship and sometimes post-doc positions these “junior” KOLs are usually on average 15 years post medical school.
Another one would be physicians, researchers, or other specialists that represent diverse patient populations. Forging connections with these types of experts will help increase the availability of trials to underserved populations and gain a better understanding of how well the drug may help patients affected by the disease.
Finally, there is a type we refer to as uncut GEMS (general expert and meaningful stars). These are doctors who are not (yet) KOLs, but have significant experience in a given therapeutic area with an established academic and treatment career. They can bring fresh ideas and diversity of thought to the table, but still need the opportunity to break through and have their research recognized.
FAQ: How can I find these KOLs?
Answer: It can be tricky to track and understand the digital or social media activities of new KOLs. MSLs have to change the way they do their due-diligence to find thought leaders and digital influencers, otherwise these KOLs will be missed.
We find this simple, five-step exercise is a great place to start:
Do a two-week look back on one social channel with a few providers to understand who even has a social media presence.
Pick three to five who do have social media profiles, and spend some time analyzing them to get a feel for their activity and level of influence.
Create a grid or spreadsheet with the names of the doctors and these parameters: how many people they are connected to, who they are following, who they are followed by (gives glance of reach), how many times they have shared content, how many times they have engaged with content via a reaction like a thumbs up or a like, and so on.
Fill out the grid and look for any patterns that might emerge. Are they “social scientists” who often respond and engage? Are they “silent scholars” who don’t engage much? Or are they “somewhat salient” and only engage sometimes? This will give insight into how to approach them.
Look ahead at your organization’s initiatives for the next 6-12 months and consider how your new understanding of these DOLs might change your strategies. Could they be beneficial to connect with? Will they add diversity to your trial landscape?
A great bell-weather is to look at who they are networked with and how often they are cited by other experts, and a data-driven network can help filter this. MSLs can leverage technology to help, and there are AI-driven platforms out there that maintain up-to-date KOL profiles including social content. These tools can give insight into these rising experts and their spheres of influence, rank experts, monitor social conversations, and help tailor communications.
FAQ: OK, I’ve identified some new KOLs. Now what?
Answer: The way in which MSLs engage with KOLs is evolving as we emerge from the pandemic. New research shows that nearly 38% of MSLs said moving to virtual meetings with KOLs had a negative impact on their job, and 70% of MSLs prefer to go back to in-person meetings in a post-Covid world.
During the height of the pandemic, MSLs and medical affairs had to get creative in how they connected with KOLs. Gone were the days of in-person meetings, and relationship building went digital. But now the pendulum is swinging back and in-person engagements are once again trending.
Recent data tells us that both MSLs and KOLs prefer in-person interactions. But regardless of how you connect with these emerging KOLs, personalization will be key. Considering that the majority of meetings between MSLs and KOLs last less than 30 minutes, it’s important to make an impact. If you can gather information on what KOLs are discussing and where, and use that insight to tailor the conversation, you can make the most of your limited time.
Photo: oatawa, Getty Images

Butler Health System and Excela Health, both based in Pennsylvania, finalized their merger January 1. The two health systems have come together to form a five-hospital system that is now the third largest in the state, following UPMC and Allegheny Health Network.
The new health system will generate more than $1 billion in revenue and serve a population of 750,000 in western Pennsylvania. The new entity will employ about 7,300 people and have more than 1,000 physicians and practitioners, Butler and Excela said.
The five hospitals operated by the new entity span three Pennsylvania counties. They are in the following cities: Butler, Clarion, Mount Pleasant, Latrobe and Greensburg.
The organizations initially announced their plan to merge in June and signed a definitive agreement to merge in November. The definitive agreement and other legal documents have been submitted to the state and federal government for review, the health systems said.
The merger comes at a financially challenging time for both organizations. Butler reported an operating loss of $5.9 million on operating revenue of $114 million for the third quarter of 2022, and Excela reported an operating loss of $2 million on operating revenue of $163 million for the same period, the Pittsburgh Post-Gazette reported.
Ken DeFurio, Butler’s CEO, will serve as CEO of the new health system. John Sphon, Excela’s CEO, will retire in March. He will stay on as an advisor for several months and will remain a trustee of the new entity.
“This was a crucial step in bringing the two organizations together,” DeFurio said in a statement. “Over the past year, both boards invested an immense amount of work, time and energy to determine if this merger made sense. We now look forward to implementing the opportunities that we’ve identified and discovering new ones.”
Sphon agreed, calling the merger a “watershed moment” in the history of both organizations.
The new health system does not have a name yet. However, Butler and Excela have said that they plan to release more information about the new entity — including its name — in the “next few weeks.”
Both organizations stressed that while the deal is now closed, there is still a lot of work to be done to create the new integrated health system.
“It is important to underscore that a merger process of this magnitude is very complex and requires an approach that is highly thoughtful and diligent,” DeFurio said in a statement. “We can now continue our focus on integrated governance, executive structure and other elements that are key to effective and efficient delivery of care.”
The deal made by Butler and Excela is the first hospital merger to be completed in 2023. Some of the biggest hospital mergers completed last year were the deals made between Atrium Health and Advocate Aurora Health and between Intermountain Healthcare and SCL Health.
Photo: Dmitrii_Guzhanin, Getty Images